1–2 Week Checks: Clinician Protocol for Phentermine With Semaglutide

1–2 Week Checks: Clinician Protocol for Phentermine With Semaglutide

Phentermine and semaglutide can be combined, but only when a clinician recommends it and monitors you closely, because formal trial evidence for the pairing is limited and the side-effect risk is higher than with either drug alone. This is not a combination to start on your own. The sections below walk through what each drug does, when clinicians consider layering them, and what monitoring should look like if your care team decides it’s worth trying.
TL;DR:
- Combining phentermine with semaglutide is only recommended under strict medical supervision because there is limited trial evidence and increased side-effect risks.
- Phentermine acts as a short-term stimulant to suppress appetite, while semaglutide provides long-term weight management by reducing hunger and slowing gastric emptying.
- The typical weight loss from semaglutide in clinical trials is around 15% of body weight over 68 weeks, which exceeds what phentermine achieves alone.
- Risks from the combination include hypoglycemia, cardiovascular strain, dehydration, and thyroid issues, especially in patients with preexisting conditions or contraindications.
- Proper monitoring involves baseline assessments, frequent follow-ups, and diligent management of side effects, making self-prescription unsafe and requiring clinician involvement.
GlpcareGet Personalised Weight Management SupportGLPCare combines clinician support, semaglutide care, nutrition coaching, and health insights from a wearable device.Explore GLPCare
Table of Contents
- What Phentermine Is and Why It’s a Short-Term Tool
- Semaglutide: How It Works and What Its Boxed Warning Covers
- Can You Take Phentermine and Semaglutide Together?
- What the Evidence Actually Shows About Results
- Risks, Side Effects, and Who Should Avoid This Combination
- The Monitoring Protocol Behind Safe Combination Therapy
- Managing Side Effects Day to Day
- Planning for the Long Term After Phentermine Ends
- A Clinician’s Note on Shared Decision-Making
- How GLPCare Supports Supervised Semaglutide Care
- Sources
- FAQ
What Phentermine Is and Why It’s a Short-Term Tool
Phentermine is a sympathomimetic appetite suppressant, meaning it works on the central nervous system to reduce hunger signals in a way similar to amphetamine-class stimulants. It’s sold under brand names like Adipex-P and as a generic, typically taken once daily in the morning. The Adipex-P prescribing information indicates it as a short-term adjunct to diet and exercise for weight reduction, not a long-term maintenance drug.
That “short-term” framing matters clinically. The same label states that combining phentermine with other weight-loss drugs has not been established as safe or effective, which is part of why any pairing with semaglutide needs a clinician’s judgment call rather than a standard prescription.
Because phentermine stimulates the cardiovascular and nervous systems, its label carries specific cautions clinicians watch for:
- Increased heart rate and blood pressure, requiring caution in anyone with existing cardiovascular disease.
- A contraindication with monoamine oxidase inhibitors (MAOIs), due to risk of a hypertensive crisis.
- Possible psychiatric effects, including insomnia, anxiety, or irritability, especially with evening dosing.
Clinicians prescribing phentermine alongside another weight-loss therapy generally check baseline heart rate and blood pressure first, then recheck at follow-up visits to catch early warning signs before they become a bigger problem.
Semaglutide: How It Works and What Its Boxed Warning Covers
Semaglutide belongs to the GLP-1 receptor agonist class. It slows gastric emptying, reduces appetite, and improves glycemic control, which is why it’s approved both for chronic weight management (Wegovy) and for type 2 diabetes (Ozempic). Most formulations are weekly injections, though an oral version exists with strict dosing instructions.
The Wegovy prescribing information carries a boxed warning for thyroid C-cell tumors observed in rodent studies, and the drug is contraindicated in anyone with a personal or family history of medullary thyroid carcinoma or Multiple Endocrine Neoplasia syndrome type 2. The same label explicitly warns against combining semaglutide with any other GLP-1 receptor agonist or semaglutide-containing product, a detail that matters if a patient is considering tirzepatide with phentermine instead, since the same combination logic applies.
A few practical points shape how semaglutide interacts with daily life and other medications:
- It lowers blood glucose, which raises hypoglycemia risk when paired with insulin or insulin secretagogues.
- Gastrointestinal side effects like nausea and vomiting can lead to dehydration if not managed early.
- The oral formulation must be taken on an empty stomach with no more than four ounces of water, then followed by a 30-minute fasting window before food, drink, or other oral medications, since slowed gastric emptying can affect how those medications absorb.
Dosing typically escalates over weeks to reach a maintenance level, and most people stay on semaglutide long after any short-term appetite suppressant would have been discontinued.
Can You Take Phentermine and Semaglutide Together?
There’s no documented pharmacokinetic drug interaction between phentermine and semaglutide, meaning the two don’t compete for the same metabolic pathways in a way that changes blood levels of either drug. That’s different from saying the combination is proven safe. No large randomized controlled trial has tested phentermine and semaglutide together for either safety or effectiveness, which is why using phentermine with semaglutide is considered off-label combination therapy rather than a standard protocol.
Clinicians who do consider adding phentermine to a semaglutide regimen typically have one of a few scenarios in mind:
- A weight-loss plateau on GLP-1 therapy alone, where appetite suppression from semaglutide has leveled off and a clinician wants a short-term boost.
- A brief transition period, such as while a patient waits for GLP-1 dose escalation to take effect and needs additional appetite control in the interim.
- A patient with no cardiovascular contraindications who has tolerated each drug individually and wants to test a combined approach under supervision.
None of these scenarios override the core requirement: mandatory clinician oversight and informed consent. Because both drugs can independently raise heart rate, cause gastrointestinal upset, or affect mood and sleep, the additive risk needs to be spelled out to the patient before starting, not discovered afterward. A Drugs notes that patients managing diabetes with semaglutide face increased hypoglycemia risk when phentermine is added, which is one of the clearer, evidence-backed reasons glucose monitoring has to be part of the plan rather than an afterthought.
If you’re currently on Ozempic and considering phentermine, or already using Wegovy and wondering about phentermine and Wegovy together, the honest answer is that your prescriber needs to evaluate your specific cardiovascular and metabolic history before making that call.
What the Evidence Actually Shows About Results
Semaglutide’s own trial data sets a high bar. In the pivotal STEP trials reviewed in clinical literature on GLP-1 and tirzepatide therapies, semaglutide 2.4 mg produced average weight loss of about 15% of body weight over 68 weeks in a trial setting, substantially more than what short-term stimulant anorectics like phentermine have historically delivered on their own.
Semaglutide’s average weight loss in the STEP trials reached roughly 15% of body weight over 68 weeks, as detailed in Semaglutide for Weight Loss: What the Evidence Shows, a benchmark that dwarfs what short-term appetite suppressants typically produce in isolation.
Phentermine alone tends to produce modest short-term weight loss, generally sought as a jump-start rather than a lasting solution, which is consistent with its short-term labeling. The gap between the two drug classes is part of why some clinicians consider layering phentermine onto a semaglutide plan during a plateau: the GLP-1 does the heavy lifting long-term, and phentermine is meant as a temporary nudge.
What’s missing from this picture is combination-specific evidence. Everything known about phentermine plus semaglutide together comes from real-world clinical use and case-by-case reports, not from large randomized trials designed to test the pairing itself. That’s an important distinction for anyone using phentermine semaglutide weight loss claims found online as a reason to self-medicate. The absence of trial data doesn’t mean the combination is unsafe, but it does mean your clinician is making an individualized judgment call rather than following an established protocol.

Risks, Side Effects, and Who Should Avoid This Combination
Layering two active medications means layering two sets of risks, and some of those risks compound rather than simply add up.
- Hypoglycemia, particularly in patients also taking insulin or sulfonyl ureas, since semaglutide already lowers blood glucose and appetite suppression from phentermine can mask early warning signs like shakiness or confusion.
- Cardiovascular strain, since phentermine’s stimulant effect on heart rate and blood pressure needs closer watching in anyone with uncontrolled hypertension, arrhythmia history, or other heart disease.
- Dehydration and kidney stress, because semaglutide’s gastrointestinal side effects, especially vomiting and diarrhea, can lead to volume depletion. The FDA’s semaglutide labeling notes postmarketing reports of acute kidney injury tied to this kind of fluid loss, which is why renal function gets monitored if GI symptoms turn severe.
- Thyroid risk, carried specifically by semaglutide’s boxed warning for medullary thyroid carcinoma and MEN2, unrelated to phentermine but still a hard contraindication for anyone with that personal or family history.
Beyond these, several conditions rule the combination out entirely: pregnancy or breastfeeding, recent MAOI use, a history of pancreatitis, and severe uncontrolled psychiatric illness. Anyone in these categories should not be considered for combined therapy regardless of how well either drug is tolerated individually.
Pro Tip: Keep a simple daily log of blood pressure, resting heart rate, and any GI symptoms during the first few weeks of combination therapy. It gives your clinician a clearer picture at your next visit than a memory of “I felt off sometimes.”
The Monitoring Protocol Behind Safe Combination Therapy
A responsible combination plan doesn’t start with a prescription. It starts with a baseline workup and a documented monitoring schedule.
- Baseline evaluation: pregnancy test where relevant, a review of personal and family thyroid or MEN2 history, baseline blood pressure and heart rate, and baseline renal function labs.
- Glucose monitoring plan: for anyone on insulin or a secretagogue, daily glucose logs during the first weeks of any dose change, with pre-planned adjustments to antidiabetic medication if hypoglycemia signs appear.
- Renal monitoring triggers: if a patient develops persistent vomiting or diarrhea, renal function gets rechecked promptly, since postmarketing data links volume depletion from GI side effects to acute kidney injury.
- Follow-up cadence: a check-in at one to two weeks after any dose change, then again at four to six weeks for labs and a symptom review.
Between visits, a few practical rules keep the plan on track:
- Hydration becomes a daily priority, not an afterthought, once GI symptoms appear.
- Any new chest pain, irregular heartbeat, or severe abdominal pain pauses therapy immediately pending clinician review.
- Oral semaglutide’s fasting window (30 minutes before food, drink, or other oral medications, with no more than four ounces of plain water) gets documented and followed exactly, since absorption depends on that timing.
On the transition side, phentermine’s short-term limits mean clinicians typically plan an exit point from the start rather than an open-ended course. Some sequence the drugs instead of combining them: phentermine first for an initial jump-start, then a shift to semaglutide alone for the long haul, or the reverse when a plateau calls for a temporary boost. Whichever path is chosen, informed consent and a written monitoring plan belong in the chart before the first combined dose, not after a side effect shows up. Reviewing a general guide to semaglutide drug interactions alongside this protocol gives a fuller sense of what else can complicate the picture, including common medications many patients take without thinking twice.
Managing Side Effects Day to Day
Most of the discomfort from this combination shows up in the first few weeks, and most of it is manageable with a few adjustments.
- Nausea: smaller, more frequent meals help, along with a slower dose-escalation pace on semaglutide and, when prescribed, an antiemetic for rough patches.
- Hydration: water intake needs to increase proactively during any stretch of nausea, vomiting, or diarrhea, not just after symptoms start.
- Insomnia and anxiety from phentermine: taking the dose early in the morning and cutting caffeine after midday reduces the odds of a wired, sleepless night.
- Red flags requiring urgent attention: chest pain, a racing or irregular heartbeat, severe abdominal pain, signs of low blood sugar like confusion or trembling, or a new lump or swelling in the neck that could point to a thyroid issue.
Lifestyle habits matter just as much as the medications themselves. Adequate protein intake and resistance exercise help preserve lean muscle mass while the body is losing fat, a common concern with any GLP-1-based plan. A safety-first protocol for intermittent fasting on semaglutide is worth a look if meal timing is already a stretch with nausea in the picture, since combining fasting windows with appetite suppressants needs its own care. Realistic expectations help too: this combination is meant to support a plan already built on nutrition and movement, not replace one.
Planning for the Long Term After Phentermine Ends
Phentermine’s role in this story is temporary by design. Most clinicians limit its use to a matter of weeks to a few months, consistent with its short-term labeling, then reassess whether it’s still adding value.
Semaglutide, by contrast, is built for the long haul. Clinicians typically set expectations around months to years of maintenance therapy, since stopping a GLP-1 often leads to some regain without continued lifestyle support.
- Phentermine’s exit point is planned from day one, not decided reactively when side effects appear.
- Semaglutide continues as the maintenance backbone once any short-term stimulant phase ends.
- Nutrition coaching and resistance training take over the job of protecting results once phentermine is out of the picture.
Tapering off phentermine doesn’t require the same careful wind-down that stopping semaglutide does, but the transition still deserves a conversation with your clinician about what changes in appetite or energy to expect. A broader look at GLP-1 therapy’s evidence base for weight loss covers how clinicians typically structure that longer maintenance phase once the short-term phase wraps up.
A Clinician’s Note on Shared Decision-Making
The threshold for combining these two drugs isn’t a fixed rule. It’s a judgment built on cardiovascular history, current glucose control, and how well each drug has been tolerated alone. What matters most is that the decision gets made together, with the risks laid out plainly and a monitoring plan written down, not assumed. Every combination plan deserves its own documented rationale, because no two patients bring the same baseline risk to the table.
— Dominique
How GLPCare Supports Supervised Semaglutide Care
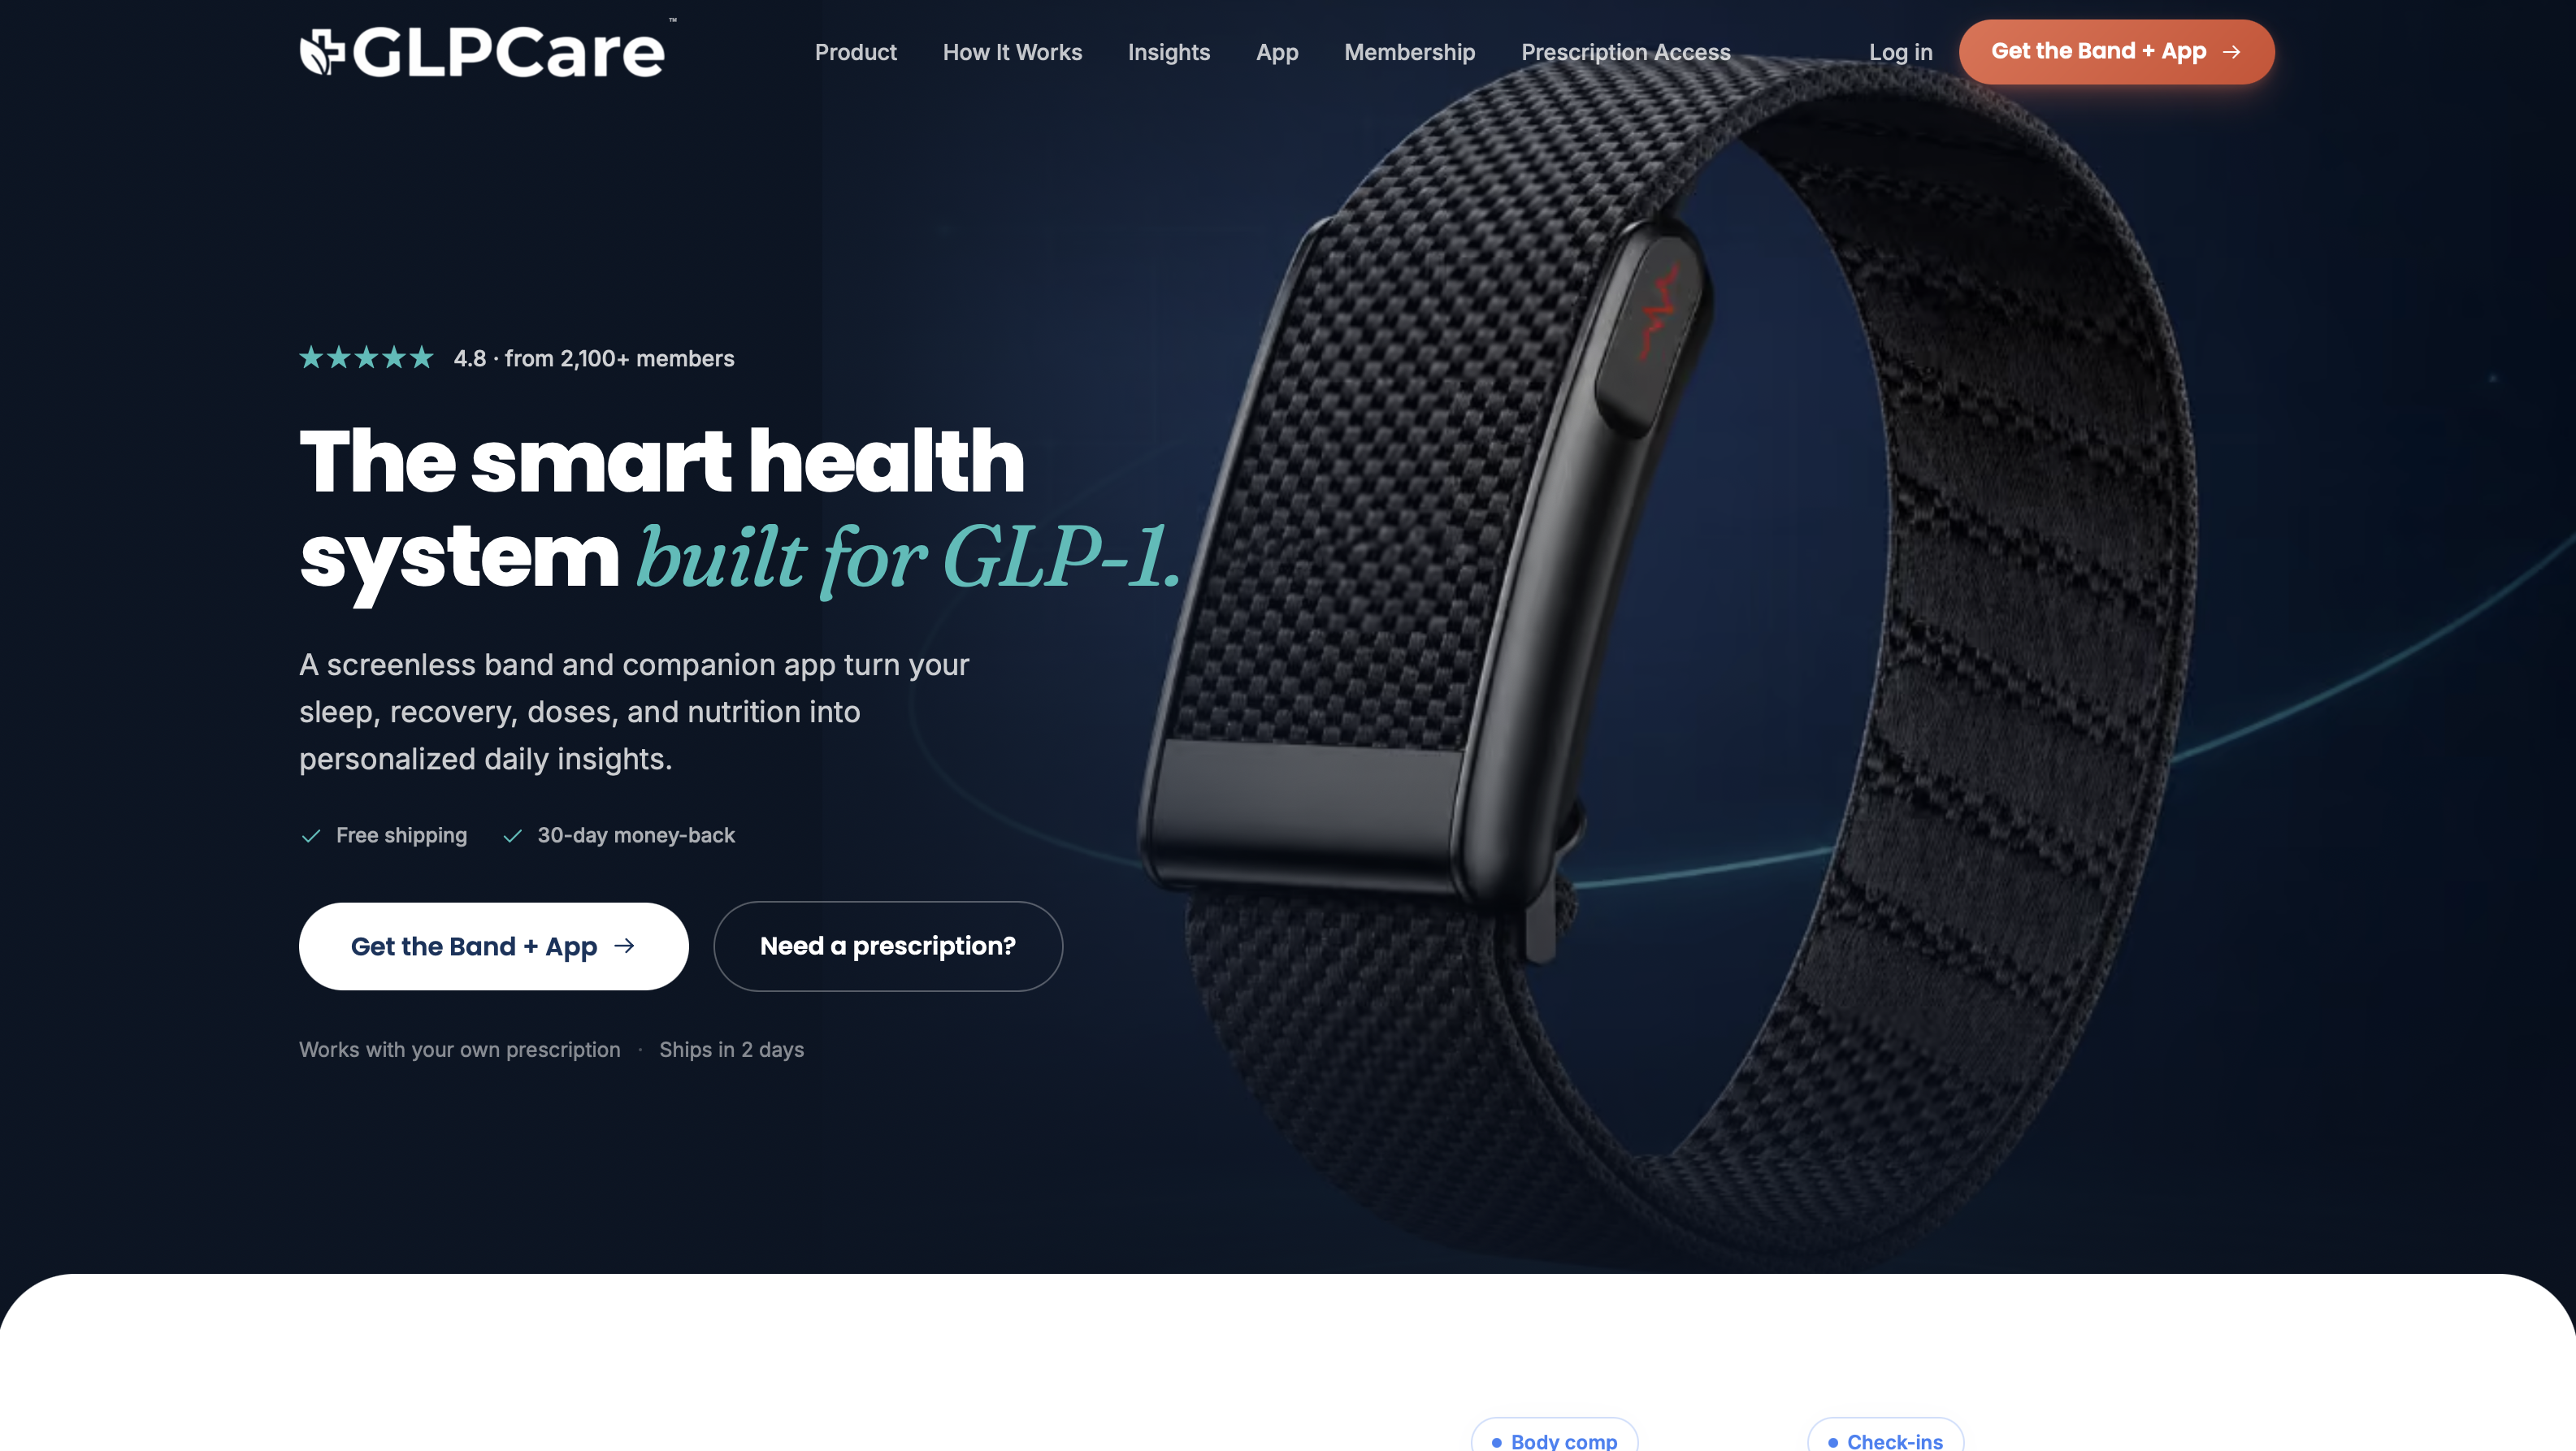
Deciding whether phentermine belongs in your plan takes more than a quick consult, and that’s the gap GLPCare is built to close. GLPCare’s Semaglutide Care plan pairs prescription GLP-1 medication with clinician oversight, personalized nutrition coaching, and a screenless wearable band that tracks heart rate, sleep, and activity in real time, so any cardiovascular or recovery changes show up before they become a problem.
- Clinician-reviewed medication management, including dose adjustments if a combination therapy is ever appropriate for your case.
- A wearable band and AI-driven app that log biometric data alongside your dosing history.
- Ongoing nutrition coaching aimed at preserving lean muscle while you lose fat.
Getting started means completing an online clinical assessment first. From there, GLPCare’s team determines whether Semaglutide Care, Tirzepatide Care, or the broader GLPCare Membership fits your history and goals, plans start at $209 per month for Semaglutide Care. An individualized medical evaluation is what ultimately decides if any combination therapy makes sense for you.
Sources
- Drugs
- Phentermine (Adipex-P) prescribing information (FDA)
- Pivotal GLP-1 and tirzepatide trials and reviews (PMC article)
This article is general information, not a substitute for advice from a qualified doctor. Consult a qualified healthcare professional about your own circumstances before acting on anything here.
FAQ
Can you take phentermine with a semaglutide?
Yes, but only under a clinician’s supervision, since there’s no established safety or efficacy data for the combination and both drugs carry their own risks that can compound. A prescriber needs to review your cardiovascular history, glucose control, and current medications before considering it.
How much weight can you lose on phentermine and semaglutide?
There’s no large trial measuring weight loss from the combination specifically, so any figure would be anecdotal rather than established. Semaglutide alone has produced average weight loss of about 15% of body weight over 68 weeks in trial settings, while phentermine tends to add a modest short-term effect on top when a clinician includes it.
Is it safe to take Ozempic and phentermine together?
It can be done safely for some patients, but only with clinician oversight, since combining phentermine with other weight-loss drugs lacks established safety data according to phentermine’s own labeling. Blood pressure, heart rate, and glucose monitoring all become part of the plan if a prescriber decides to move forward.
What not to mix with semaglutide?
Semaglutide should never be combined with another semaglutide-containing product or GLP-1 receptor agonist, including tirzepatide, per its prescribing information. It also requires caution with insulin or insulin secretagogues due to hypoglycemia risk, and with any oral medication whose absorption depends on normal gastric emptying.