GLP-1 With Prediabetes: Who Qualifies and What to Expect

GLP-1 With Prediabetes: Who Qualifies and What to Expect

If you have prediabetes, a GLP-1 medicine such as semaglutide or tirzepatide may be an option, but not as a prediabetes treatment on its own. No GLP-1 medicine is FDA-approved for prediabetes. Clinicians prescribe them for weight management when you meet the weight criteria, and in that setting the blood sugar results in trials have been striking. This guide explains who qualifies, what the research shows, what the side effects are and what happens if you stop.
GlpcareWeight Support Beyond MedicationGLPCare brings GLP-1 therapy, personalized nutrition coaching, wearable health insights, and clinician support into one weight management program.VisitTL;DR
- GLP-1 medicines are not FDA-approved to treat prediabetes. They are prescribed for weight management, which is how most adults with prediabetes get access.
- Typical criteria are a BMI of 30 or higher, or a BMI of 27 or higher plus a related condition such as high blood pressure or high cholesterol.
- In trials of adults with prediabetes and excess weight, most people on semaglutide returned to normal blood sugar, and new type 2 diabetes cases dropped sharply.
- Stomach side effects are the most common issue, and weight and glucose benefits tend to fade after treatment stops.
- Lifestyle change remains the foundation. Medication works best inside a connected program with clinician oversight.
Table of Contents
- Can you get a GLP-1 if you have prediabetes?
- What the guidelines say about prediabetes and obesity medicine
- What trials show for people with prediabetes
- Why the timing matters: your risk of progression
- How GLP-1 medicines compare with lifestyle change
- Side effects and safe use
- What happens when you stop
- Paying for it: coverage and cost
- How GLPCare supports adults with prediabetes
- Our perspective
- A practical path to follow
- FAQ
- Sources
Can you get a GLP-1 if you have prediabetes?
Yes, in many cases, but the route matters. The FDA has not approved GLP-1 medicines to treat prediabetes, and most insurers do not cover them for that purpose. The possible exception is people who have prediabetes and obesity, according to Mayo Clinic Press.
In practice, a prescriber looks at your weight, your related conditions and your labs. Prediabetes is one important piece of that picture, not the label on the prescription.
The American Heart Association describes the usual weight-loss prescribing criteria this way:
- Obesity, meaning a BMI of 30 kg/m² or higher, or
- Overweight, meaning a BMI of 27 kg/m² or higher, plus at least one related condition such as high blood pressure or high cholesterol.
If you want a fuller walkthrough of what to gather before an assessment, our guide to GLP-1 eligibility covers it step by step. If you would rather check where you stand now, the GLP-1 readiness quiz takes a few minutes.
What the guidelines say about prediabetes and obesity medicine
The 2026 American Diabetes Association (ADA) guideline summary on obesity pharmacotherapy, as reported by Medscape, advises that adults with prediabetes should be prioritized for obesity medications with demonstrated evidence for preventing progression to diabetes: tirzepatide and semaglutide. Phentermine-topiramate, liraglutide and orlistat are listed as having potential benefit.
That is a meaningful signal. It does not make a GLP-1 a prediabetes drug by label. It does mean that when weight management is appropriate for you, the medicines with the best diabetes-prevention evidence are the ones guidelines point to first.
There is also a scientific debate about how far to take this. Researcher Mayer Davidson argued in 2023 that treating the blood sugar of prediabetes with drugs is not warranted by itself. He added that the 15% to 20% weight loss seen with high-dose GLP-1 and GLP-1/GIP medicines deserves consideration, because that much weight loss should reduce insulin resistance and lower the risk of developing diabetes.
What trials show for people with prediabetes
The strongest evidence comes from people who had prediabetes along with overweight or obesity.
Semaglutide and the STEP trials
A pooled analysis of the STEP 1, 3 and 4 trials followed 1,536 adults with prediabetes and overweight or obesity. At week 68, significantly more people on semaglutide 2.4 mg had normal blood sugar than on placebo.
| Trial | Semaglutide 2.4 mg | Placebo |
|---|---|---|
| STEP 1 | 84.1% | 47.8% |
| STEP 3 | 89.5% | 55.0% |
| STEP 4 | 89.8% | 70.4% |
All differences were statistically significant (P < 0.0001). Semaglutide also brought greater improvements in HbA1c, fasting plasma glucose and insulin resistance (HOMA-IR).
The smaller STEP 10 trial enrolled 207 adults with obesity and prediabetes. After 52 weeks, 81% of those on semaglutide had normal glucose control, compared with 14% on placebo.
A look across 12 trials
A 2024 systematic review and meta-analysis pooled 12 trials with 2,903 people on GLP-1 medicines and 1,413 controls. GLP-1 medicines significantly increased the chance that prediabetes reversed to normal blood sugar (relative risk 1.76) and reduced new-onset diabetes (relative risk 0.28). They also lowered HbA1c, fasting glucose, body weight, waist circumference, triglycerides and LDL cholesterol.
Tirzepatide and liraglutide
A 2026 review in Diabetes Therapy reported that with liraglutide over three years, only 3 people needed to be treated for one to reach normal blood sugar. For tirzepatide, 89.9% to 93.3% of users reached normal glucose across doses, compared with 58.9% on placebo.
Heart protection
In the SELECT trial, semaglutide lowered the combined risk of cardiovascular death, nonfatal heart attack or nonfatal stroke (hazard ratio 0.80). A prespecified analysis found the benefit did not depend on baseline HbA1c, which supports a benefit for people with prediabetes, according to a 2026 evidence review. Note that SELECT enrolled adults with established heart disease and excess weight, so it speaks to that group.
Why the timing matters: your risk of progression
Prediabetes does not always become diabetes. In an AHA-reported analysis of adults aged 18 to 40, the five-year risk of progressing to type 2 diabetes was 7.5% overall. It rose to 10.9% among those who met criteria for GLP-1 treatment for weight loss. It reached 24.8% for those who also had higher fasting glucose (110 to 125 mg/dL).

This is why a clinician looks past the prediabetes label. Weight, fasting glucose, blood pressure and cholesterol together tell you far more about your direction of travel than one lab value does.
How GLP-1 medicines compare with lifestyle change
Lifestyle change is still the best-studied way to prevent type 2 diabetes. The Diabetes Prevention Program found that intensive lifestyle intervention reduced the incidence of type 2 diabetes by 58%, while metformin reduced it by 31%, as summarized in the 2024 meta-analysis. The program aimed for 7% weight loss and at least 150 minutes a week of moderate activity.
The American Family Physician notes that programs combining diet, weight loss and exercise reduce type 2 diabetes diagnoses by up to 58% over three years. Metformin has the strongest medication evidence, and liraglutide has some evidence of benefit.
The useful way to think about it is not medicine versus habits. A GLP-1 reduces appetite so that the habits are easier to keep: protein at meals, strength training, regular sleep and daily movement. The medicine and the habits work together, and the habits are what carry forward.
Side effects and safe use
The most common side effects are gastrointestinal: nausea, vomiting, diarrhea and constipation. According to the 2024 meta-analysis, these are generally dose-dependent, tend to appear while the dose is being increased and usually ease over time. In that analysis, nausea (relative risk 2.47), vomiting (3.54) and diarrhea (1.69) were all more common with GLP-1 medicines than with control treatment.
The same review notes:
- GLP-1 medicines have been linked to a higher risk of gallstones and other gallbladder events.
- Acute pancreatitis has been reported, though large trials have not shown a consistent, meaningful increase in risk.
- Low blood sugar is uncommon when a GLP-1 is used alone, but the risk goes up when it is combined with insulin or sulfonylureas.
- Labels for this drug class list personal or family history of medullary thyroid carcinoma or MEN 2 as contraindications.
- Regular monitoring of A1C, blood glucose and weight is recommended.
Tell your clinician about your full medical history, including thyroid conditions, pancreatitis, gallbladder disease and every medicine you take, before starting. Report severe or persistent stomach pain, repeated vomiting or signs of dehydration to your prescriber promptly.
If stomach symptoms show up, our guides to nausea on GLP-1 medications and diarrhea on GLP-1 medications explain why they happen and what usually helps. The broader overview is in GLP-1 side effects, explained.

What happens when you stop
The benefits depend on staying on a plan. In STEP 10, people who stopped semaglutide after 52 weeks were followed for 28 more weeks. They regained about 6.0% of their original body weight, according to DiabetesontheNet. At week 80, 44% of the semaglutide group still had normal glucose, compared with 18% on placebo. Progression to type 2 diabetes was 2.5% versus 8.3%.
The STEP 1 extension showed a similar pattern. Of the 17.3% weight loss at week 68, 11.6% was regained after stopping, leaving a net loss of 5.6%, as reported in Diabetes Therapy.
The takeaway is practical: plan the end of treatment at the start. A gradual taper, a maintenance routine and continued tracking all matter. Our guide on how to taper semaglutide safely covers the approach.
Paying for it: coverage and cost
Because prediabetes alone is not a labeled indication, coverage often hinges on whether you meet the weight criteria and what your plan includes. Our overview of GLP-1 insurance coverage explains what to ask your insurer. If your plan does not cover it, a membership model with transparent monthly pricing is one alternative.
If you are also managing PCOS alongside blood sugar concerns, PCOS diagnosis and treatment is worth reading as well, since that is a conversation to have with your clinician.
How GLPCare supports adults with prediabetes
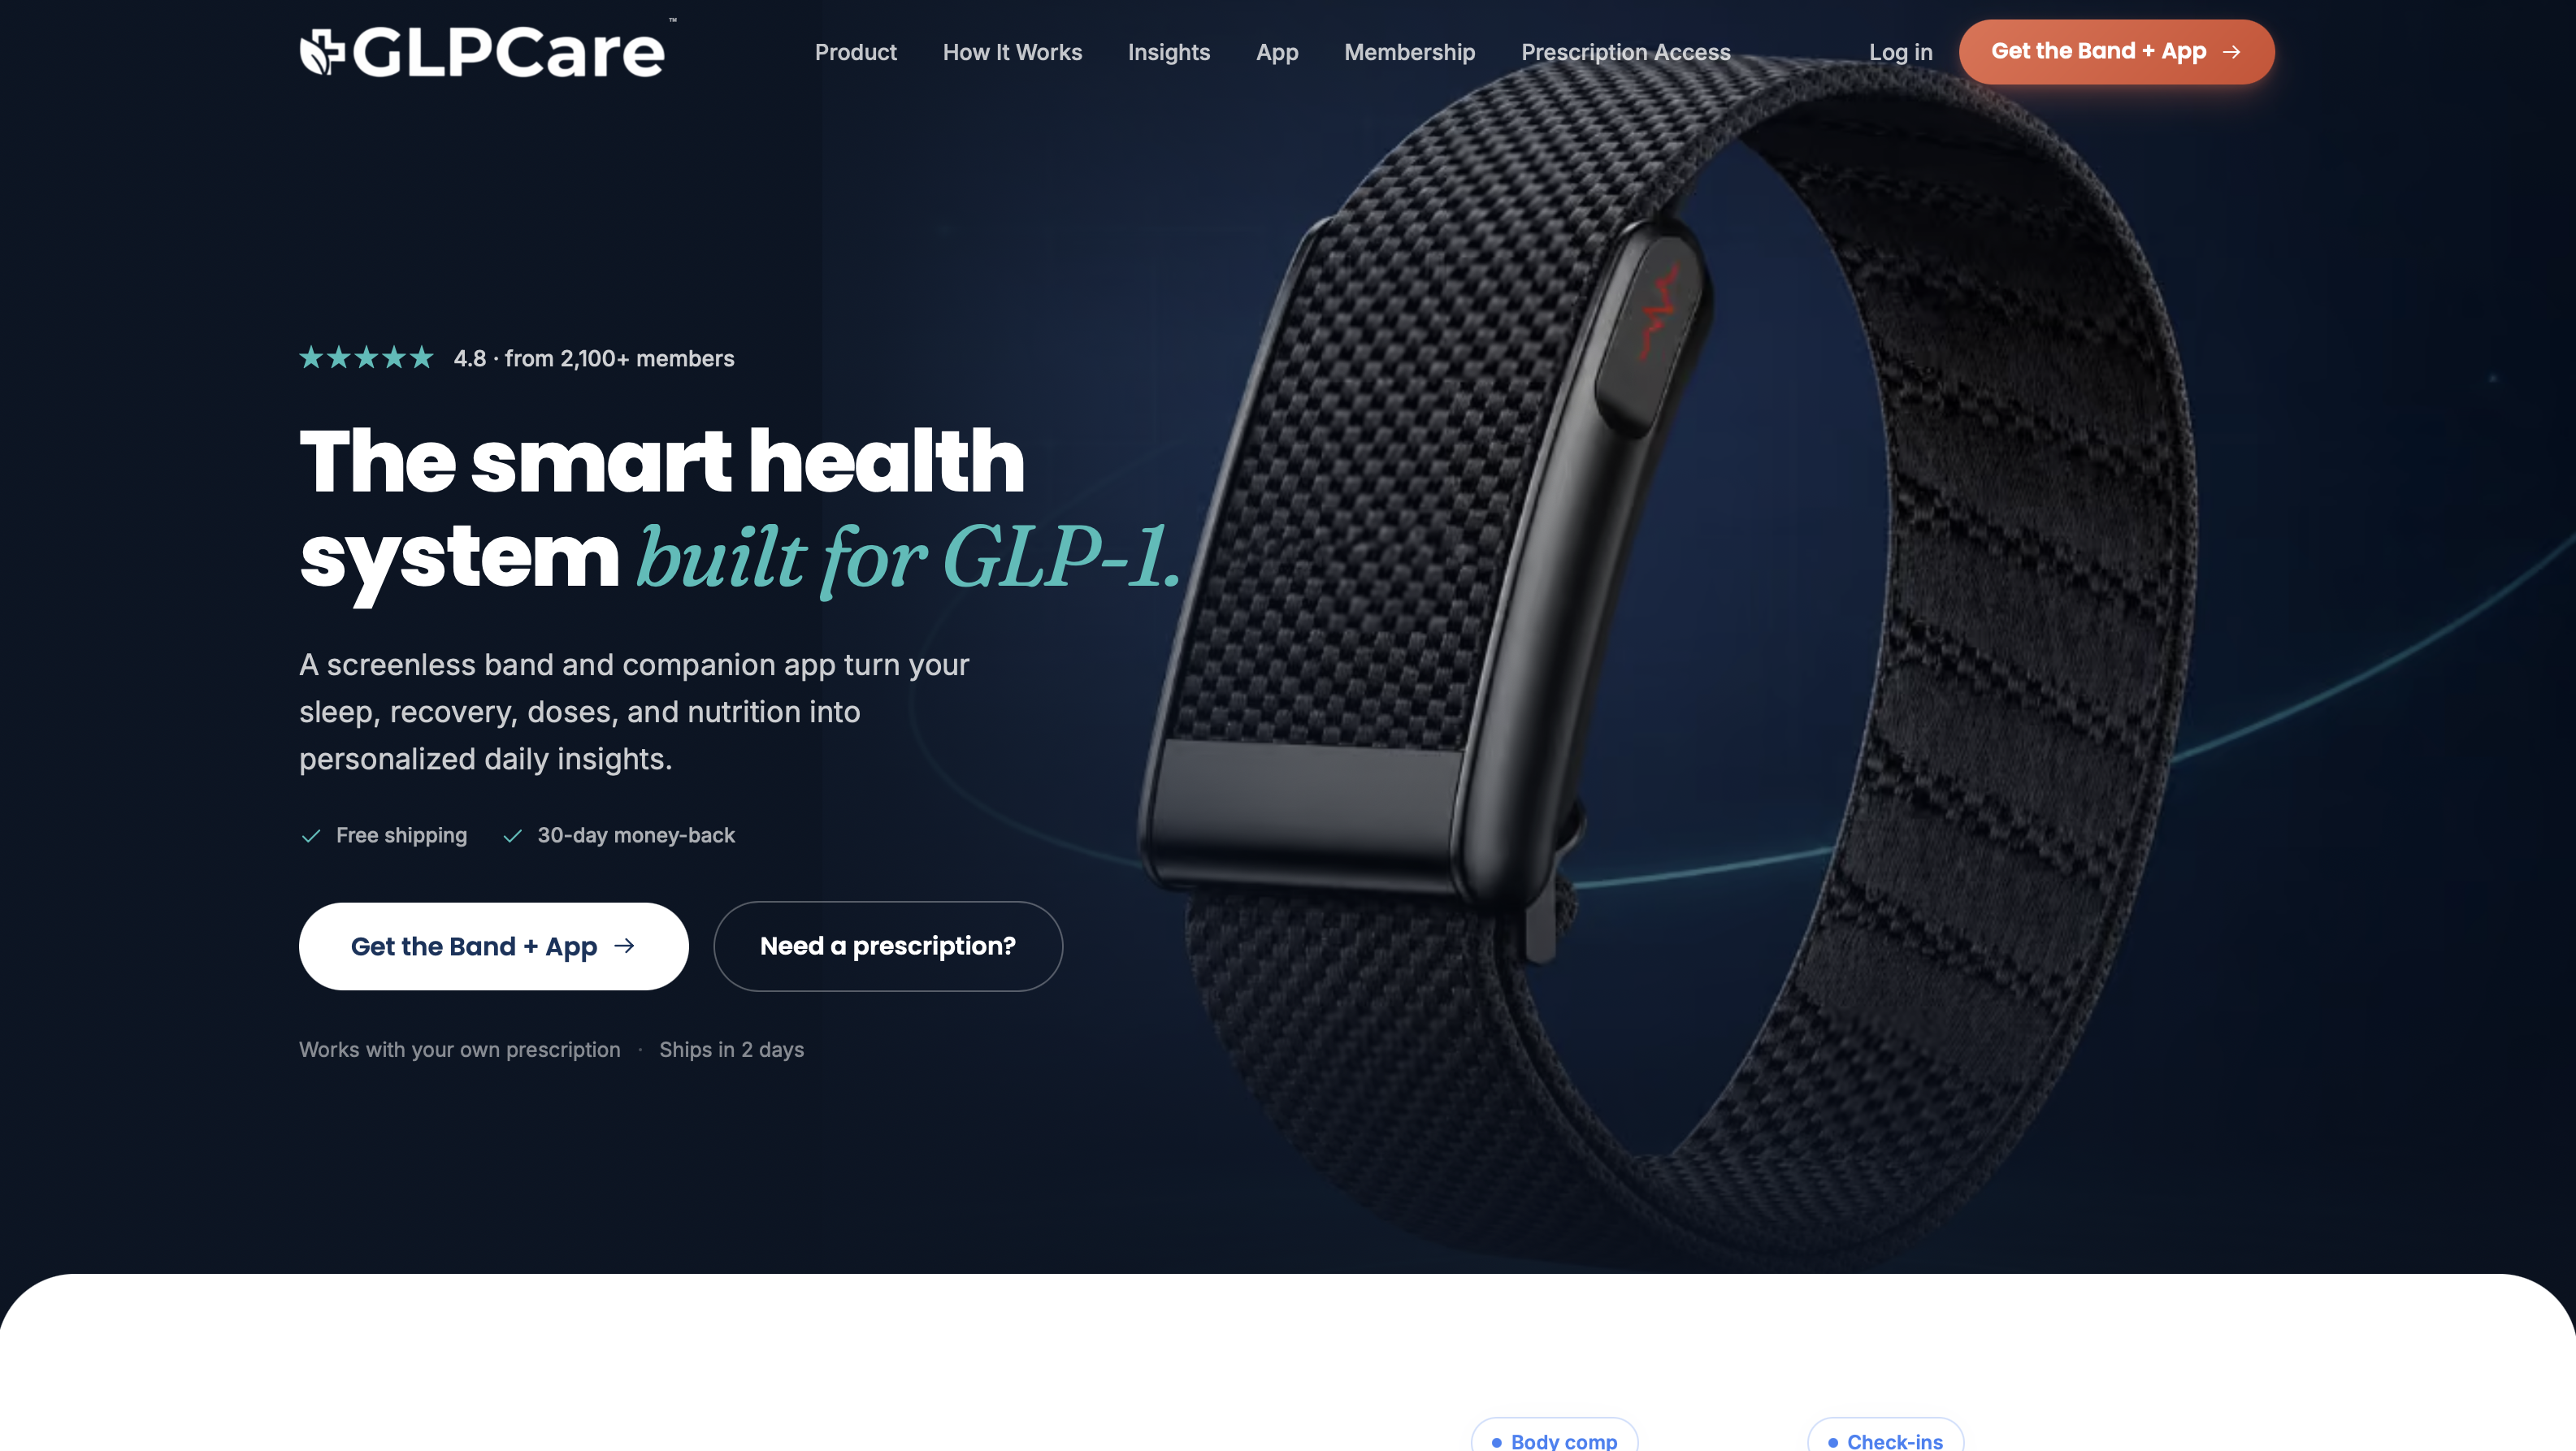
GLPCare is an integrated GLP-1 care system. It combines clinician oversight of your medication, personalized nutrition coaching, an AI-driven app for dose and progress tracking, and a screenless fitness band that tracks sleep, heart rate and activity. Our approach is designed to help you lose weight while minimizing muscle loss, with plans for people with or without an existing GLP-1 prescription.
Published pricing:
- GLPCare Membership: $199 per year. See the membership.
- Semaglutide Care: from $209 per month. Learn more about compounded semaglutide prescribed online.
- Tirzepatide Care: from $299 per month. Learn more about compounded tirzepatide prescribed online.
Prescribing always follows a clinical assessment. Our clinicians decide whether a GLP-1 is appropriate for you and which one. Our program is also backed by a money-back guarantee. If you want to compare therapies first, our GLP-1 therapy evidence guide and the page on GLP-1 for non-diabetics are good starting points.
Our perspective
Prediabetes is a window, not a verdict. Many adults hear the word from a lab report and leave with a pamphlet and little else. We think that is a missed chance.
When weight is part of the picture, a GLP-1 can make healthy habits feel achievable, perhaps for the first time. But a prescription alone is thin support. What changes outcomes is the connected system around it: a licensed clinician who reviews your dose, nutrition coaching that protects muscle, and daily data on sleep, heart rate and activity, so every visit starts with a clearer picture.
That is why we built GLPCare as one integrated program. Your medication, your habits and your recovery data sit in one place, and your care team can act on all of them. Our aim is progress you can keep, including a plan for what comes after the medication.
Dominique
A practical path to follow
- Get current labs. Ask for A1C and fasting glucose, and note your blood pressure and cholesterol.
- Check your numbers against the criteria. Compare your BMI and related conditions with the thresholds above.
- Talk with a clinician. Share your full history, especially thyroid, pancreas and gallbladder issues.
- Build the habits alongside the medicine. Aim for protein at each meal, strength training and regular walking.
- Track and recheck. Follow your weight, glucose and how you feel, and repeat labs on your clinician’s schedule.
- Plan for the long term. Decide early how you will maintain results if you reduce or stop medication.
FAQ
Can I get semaglutide if I am prediabetic?
Possibly. Semaglutide is not FDA-approved for prediabetes itself, but it is approved for weight management in adults who meet weight criteria. If you have prediabetes along with obesity, or overweight plus a related condition, a clinician may prescribe it. Insurance coverage is less certain in that situation.
Can a GLP-1 reverse prediabetes?
In trials, most adults with prediabetes and excess weight returned to normal blood sugar while on semaglutide, for example 84.1% versus 47.8% on placebo in STEP 1. Results depend on staying on treatment and keeping up lifestyle changes. Part of the benefit fades after stopping, so talk with your clinician about a maintenance plan.
Is lifestyle change enough instead of medication?
For many people, structured lifestyle change is very effective. The Diabetes Prevention Program cut type 2 diabetes incidence by 58%. A GLP-1 is an option for adults who meet weight criteria and want added support, and it works best alongside the same habits.
What side effects should I expect?
Nausea, vomiting, diarrhea and constipation are the most common, especially while the dose is increasing. They usually ease over time. Call your clinician about severe abdominal pain, persistent vomiting or dehydration.
Sources
- Does Ozempic help with prediabetes? (Mayo Clinic Press)
- Type 2 diabetes risk varied widely among adults 18-40 with prediabetes (American Heart Association)
- Obesity, Pharmacologic Treatment: ADA 2026 Guideline Summary (Medscape)
- Should Prediabetes be Treated Pharmacologically? (PMC)
- Changes in Glucose Metabolism and Glycemic Status With Semaglutide (PMC)
- Diabetes Distilled: STEP 10 in prediabetes (DiabetesontheNet)
- Efficacy and safety of GLP-1 receptor agonists in prediabetes (PMC)
- GLP-1 Receptor Agonists: Their Potential in prediabetes (Diabetes Therapy)
- Semaglutide and tirzepatide in prediabetes (Primary Care Diabetes)
- Prevention or Delay of Type 2 Diabetes Mellitus (American Family Physician)