Appetite Too Low on Semaglutide? Protect Muscle With 20–30g Protein

Appetite Too Low on Semaglutide? Protect Muscle With 20–30g Protein

Decreased appetite is one of semaglutide’s expected effects, but a complete inability to eat or drink is not something to ride out quietly. If you cannot keep fluids down, are losing weight rapidly, feel faint when standing, or notice severe weakness, contact your clinician today or seek emergency care. In the meantime, lean on protein- and calorie-dense liquids or soft foods, and check in with your prescriber if intake stays inadequate for more than a few days.
TL;DR:
- Continued inability to keep fluids down, rapid weight loss, or severe weakness after four to six weeks indicates a need for medical review and potential dosage adjustment.
- Persistent low appetite increases the risk of muscle loss, nutrient deficiencies, dehydration, and long-term metabolic and health consequences if not addressed promptly.
- Prioritize small, protein-rich meals and calorie-dense liquids, with a focus on hydration, bland foods, and gradual intake to mitigate gastrointestinal side effects.
- Monitoring signs of dehydration, such as dark urine or dizziness, is essential, especially when gastrointestinal symptoms impair fluid and food intake.
- Clinician-managed programs with ongoing oversight can prevent muscle loss and nutritional deficiencies through personalized nutrition coaching and real-time health data tracking.
Glpcareglpcare.orgSupport for Safer Weight ManagementGLPCare combines GLP-1 therapy, personalized nutrition coaching, clinician support, and wearable health insights to help manage weight responsibly.Visit GLPCare
Table of Contents
- Why semaglutide reduces appetite: mechanisms and typical timing
- Nutritional and body-composition consequences of eating too little on GLP-1s
- How to tell if your low appetite is mild or needs medical review
- Practical nutrition tactics when you’re not hungry
- Exercise and simple strength routines to preserve muscle when intake drops
- Medication safety steps and clinician-managed options
- How clinician-led programs combine monitoring, nutrition coaching, and wearable data
- Psychological impacts of reduced appetite and coping strategies
- Impact of low appetite on blood sugar control in diabetic patients
- Long-term implications of sustained low appetite on overall health and metabolism
- What actually matters when appetite disappears on semaglutide
- If you want supervised care: GLPCare membership and semaglutide care
- FAQ
- Sources
Why semaglutide reduces appetite: mechanisms and typical timing
Semaglutide works on GLP-1 receptors in the brain’s appetite centers while also slowing how fast food leaves your stomach. That combination is exactly why you feel full faster and crave less between meals. The FDA prescribing information lists decreased appetite alongside nausea, vomiting, diarrhea, abdominal pain, and constipation as among the most frequent effects, and it specifically notes that semaglutide delays gastric emptying.
Nausea and early satiety often travel together. When your stomach empties more slowly, smaller amounts of food sit there longer, which triggers fullness signals before you’ve eaten much at all. Dose increases tend to intensify this pattern, since your body has less time to adjust before the next step up.
For most people, the timeline looks like this:
- Appetite suppression typically begins within days of starting semaglutide or raising the dose.
- Symptoms often peak during the first one to two weeks after a dose change.
- Many people notice gradual improvement or adaptation over the following weeks.
- Appetite that remains completely absent beyond four to six weeks at a stable dose is a signal worth discussing with your clinician rather than waiting out.
That last point matters because the goal of treatment is reduced hunger, not an inability to eat at all. One state does not automatically lead to the other.
Nutritional and body-composition consequences of eating too little on GLP-1s
Appetite suppression that goes too far has real downstream effects, and the biggest one is muscle loss. A 2026 clinical review on preserving lean mass during GLP-1 therapy recommends a food-first approach built around adequate protein intake, resistance exercise, and active management of gastrointestinal side effects, specifically because inadequate intake accelerates the loss of muscle rather than just fat.
Protein is the lever that matters most here:
- Many moderately active adults on GLP-1 therapy benefit from roughly 1.0 to 1.5 grams of protein per kilogram of body weight daily.
- Falling short of that target for weeks at a time increases the share of weight loss that comes from lean tissue instead of fat.
- Persistent calorie shortfalls can also cause fatigue, slowed healing, and in severe, prolonged cases, organ stress.
The risk goes beyond the scale. Low appetite and inadequate intake on GLP-1 medications can create gaps in vitamin B12, iron, and vitamin D, especially when meals become smaller and less varied over time.
Hydration deserves its own mention. The FDA label for semaglutide flags gastrointestinal reactions, including vomiting, diarrhea, and constipation, that can compound fluid losses. Nausea makes it harder to drink enough, constipation can mask early dehydration, and the two together raise the risk of volume depletion, particularly if you’re also losing your appetite for liquids. If you notice dark urine, dizziness when standing, or a dry mouth that doesn’t resolve with small sips, treat that as a hydration problem, not just a food problem.
How to tell if your low appetite is mild or needs medical review
A short daily check can tell you whether you’re adapting normally or heading somewhere that needs attention.
- Track your weight trend, not a single day’s number, over a rolling week.
- Check urine color: pale yellow suggests adequate hydration, while dark urine is a warning sign.
- Test for lightheadedness when you stand up quickly; dizziness can signal dehydration or low blood sugar.
- Confirm you can keep down medications, including semaglutide itself and any other prescriptions.
- Notice your energy and grip strength: a sudden drop in either is more concerning than gradual fatigue.
Some worsening during the first weeks after starting or increasing your dose is expected. What is not expected is complete loss of appetite that persists past four to six weeks, or weight loss that is unusually rapid over a short period. Either of those warrants a call to your clinician, and any combination of fainting, inability to keep fluids down, or severe weakness warrants urgent care the same day.
Practical nutrition tactics when you’re not hungry
When appetite drops, the fix isn’t forcing three full meals. It’s making every small amount of food count.
Make protein the first decision, not an afterthought. Aim for at least 20 to 30 grams of protein at each eating opportunity, even if that opportunity is small. Greek yogurt, cottage cheese, eggs, a protein shake, or a few ounces of chicken or fish all get you there without requiring a large plate. JAMA Internal Medicine’s guidance for people on GLP-1 medications specifically recommends prioritizing protein in the 20 to 30 gram range per meal, alongside small frequent meals and consistent hydration, to limit muscle loss and manage side effects. For a deeper breakdown of protein targets and food choices, our guide on how much protein to eat on semaglutide walks through practical portions.
When solid food feels like too much, calorie-dense liquids close the gap:
- Smoothies blended with Greek yogurt, nut butter, and fruit pack protein and calories into a small volume.
- Soups boosted with powdered milk or an unflavored protein powder add substance without adding bulk.
- Nut butters spread thin on crackers or fruit deliver quick calories when appetite is minimal.
- Fortified meal-replacement beverages work well on days when nothing else sounds appealing.
Mayo Clinic’s guidance on supporting weight-loss medications with adequate nutrition points to the same strategy: nutrient-dense options like Greek yogurt, smoothies, and soups, paired with hydration, tend to be better tolerated than large meals during the roughest stretches of GI side effects.
For nausea specifically, cold foods are often easier to tolerate than hot ones, since they carry less aroma. Bland textures, ginger tea or ginger chews, and smaller, more frequent portions throughout the day beat trying to push through three big meals.

Pro Tip: Keep a protein shake or shelf-stable protein bar within reach at all times. On low-appetite days, “good enough and eaten” beats “ideal and skipped.”
If you’re relying on liquid nutrition most days, or you’ve lost weight faster than expected, ask your clinician about a referral to a registered dietitian. That kind of individualized support catches gaps that general advice can’t.
Exercise and simple strength routines to preserve muscle when intake drops
Nutrition protects muscle, but movement is what tells your body to keep it. Even two short resistance sessions a week can meaningfully slow lean-mass loss while you’re eating less.
- Bodyweight moves like squats, wall push-ups, and sit-to-stands work without equipment and scale easily to your energy level.
- Resistance bands are a low-cost way to add load for rows, presses, and leg exercises if you have more capacity.
- Ten to fifteen minutes is enough on low-energy days; consistency matters more than duration.
- Having a small amount of protein within an hour or two of exercise supports recovery without requiring a full meal.
If you notice new weakness, unsteadiness, or a fall, that’s a cue to involve a physical therapist or trainer experienced with supervised programs rather than pushing through alone. Our guide on preventing muscle loss on GLP-1 medications covers routines you can adapt as your appetite and energy shift.
Medication safety steps and clinician-managed options
A clinician visit for persistent low appetite usually results in one of a few adjustments rather than stopping treatment outright: slowing the pace of dose increases, pausing at your current dose longer than planned, or temporarily reducing the dose until symptoms settle. Switching the time of day you take semaglutide, or the specific formulation, can also help in some cases.
If you take insulin or a sulfonylurea, this conversation is not optional. The FDA label for semaglutide warns of increased hypoglycemia risk when combined with insulin or insulin secretagogues, and recommends considering dose reductions of those concomitant medications. Eating less while still taking a fixed insulin dose is a common setup for low blood sugar, so monitoring more closely during this period matters. Our guide to semaglutide drug interactions covers the specifics of which medications need closer attention.
Delayed gastric emptying also has implications beyond appetite. Oral medications, including some with a narrow margin between effective and harmful doses, can be absorbed differently when the stomach empties more slowly. If you take other oral prescriptions, mention this to whoever manages them.
Finally, semaglutide carries specific guidance for pregnancy and lactation. Labeling for semaglutide products recommends discontinuing the medication before a planned pregnancy, given the time needed to clear the drug from your system. If pregnancy is a possibility for you, raise this with your prescriber before starting or continuing treatment, not after.
How clinician-led programs combine monitoring, nutrition coaching, and wearable data
Supervised care catches problems earlier than self-monitoring alone, which is the gap we built our own program to close. Through GLPCare Membership, clinician oversight, personalized nutrition coaching, and a screenless wearable band work together so that a drop in activity, sleep, or heart rate variability can flag declining intake before it shows up as significant weight loss.
That kind of early signal gives your care team time to act: adjusting your dose, pausing titration, or tightening your nutrition plan before fatigue or muscle loss sets in. The goal is catching the pattern, not just reacting to the number on the scale. For more on how this approach applies specifically to appetite and nutrition during GLP-1 treatment, our blog carries ongoing coverage from our editorial team, including the analysis in this piece.
Psychological impacts of reduced appetite and coping strategies
Losing your appetite changes more than your meals. Food is wrapped up in routine, social connection, and identity, and when that disappears, some people feel relief while others feel unsettled or even guilty about not wanting to eat.
It’s common to feel anxious about “doing it wrong” if you’re not finishing meals the way you used to, or to feel isolated at social events built around food. Some people also notice irritability or low mood that’s harder to separate from the medication itself versus the lifestyle adjustment around it.
A few coping approaches tend to help. Reframe meals around nutrient density rather than volume, so a small plate doesn’t feel like failure. Tell close friends or family what’s changing, so shared meals come with less pressure to eat a “normal” amount. If low mood, anxiety, or a strained relationship with food persists, that’s worth raising with your clinician directly, since it may point to something beyond the expected adjustment period and could benefit from additional support.
The adjustment is real, and naming it tends to make it easier to manage than treating it as something to push through silently.
Impact of low appetite on blood sugar control in diabetic patients
If you manage type 2 diabetes alongside semaglutide, reduced appetite changes the math your other medications were built around. Insulin and sulfonylureas are often dosed with the expectation of a certain carbohydrate intake, so eating significantly less without adjusting those doses raises your risk of hypoglycemia.
The FDA label for semaglutide specifically flags this interaction and recommends considering dose reductions for insulin or insulin secretagogues when starting semaglutide, precisely because the combination increases low blood sugar risk. Watch for the classic signs: shakiness, sweating, confusion, or a racing heart, especially if they show up around the times you’d normally eat a meal you’ve now skipped or shrunk.

Blood sugar monitoring becomes more important, not less, during periods of low appetite. If you use a continuous glucose monitor, pay closer attention to patterns around meals you’ve reduced or missed. If you check manually, consider testing more frequently until your intake stabilizes. This is a conversation to have proactively with whoever manages your diabetes medications, not after a low blood sugar episode happens.
Long-term implications of sustained low appetite on overall health and metabolism
Short-term appetite suppression supports weight loss. Appetite suppression that stays severe for months is a different situation, and it can work against the outcome you’re actually trying to achieve.
Sustained inadequate intake shifts the composition of weight lost toward muscle rather than fat, and muscle is metabolically active tissue. Losing more of it than necessary can slow your resting metabolic rate over time, which works against long-term weight maintenance rather than supporting it. It also leaves you with less functional strength for daily activities, which matters well beyond the number on the scale.

Micronutrient gaps that persist for months, rather than weeks, raise the risk of deficiencies that take longer to correct and can affect energy, immune function, and bone health. None of this is a reason to avoid semaglutide. It’s a reason to treat persistent, severe appetite loss as a signal to adjust the plan, not as a mark of successful treatment. The people who maintain weight loss well past the first year are generally the ones who protected muscle and nutrition along the way, not the ones who ate the least.
What actually matters when appetite disappears on semaglutide
The conventional advice on this topic tends to treat appetite loss as purely a side effect to tolerate, something you grit your teeth through until it passes. That framing misses the more useful question: what is this appetite loss costing you in muscle, energy, and nutrient status while it lasts?
We think the nutrition-first framing deserves more weight than it usually gets. Hitting a protein target matters more than hitting a calorie target, and preserving the ability to do a flight of stairs without feeling wrecked matters more than a faster number on the scale. Most people fixate on the weight loss itself and treat muscle loss as an acceptable cost. It isn’t, and the research on lean-mass preservation during GLP-1 therapy backs that up clearly.
If you take one thing from this: track your strength and energy as closely as you track your weight. A scale number without that context tells you less than you think it does.
— Dominique
If you want supervised care: GLPCare membership and semaglutide care
Managing appetite loss well takes more than willpower. It takes someone watching the pattern with you, which is exactly what our model is built around. Through GLPCare Membership, you get clinician oversight paired with personalized nutrition coaching and a screenless wearable band that tracks sleep, heart rate, and activity, giving your care team an early read on how your body is handling treatment, not just a monthly weight check.
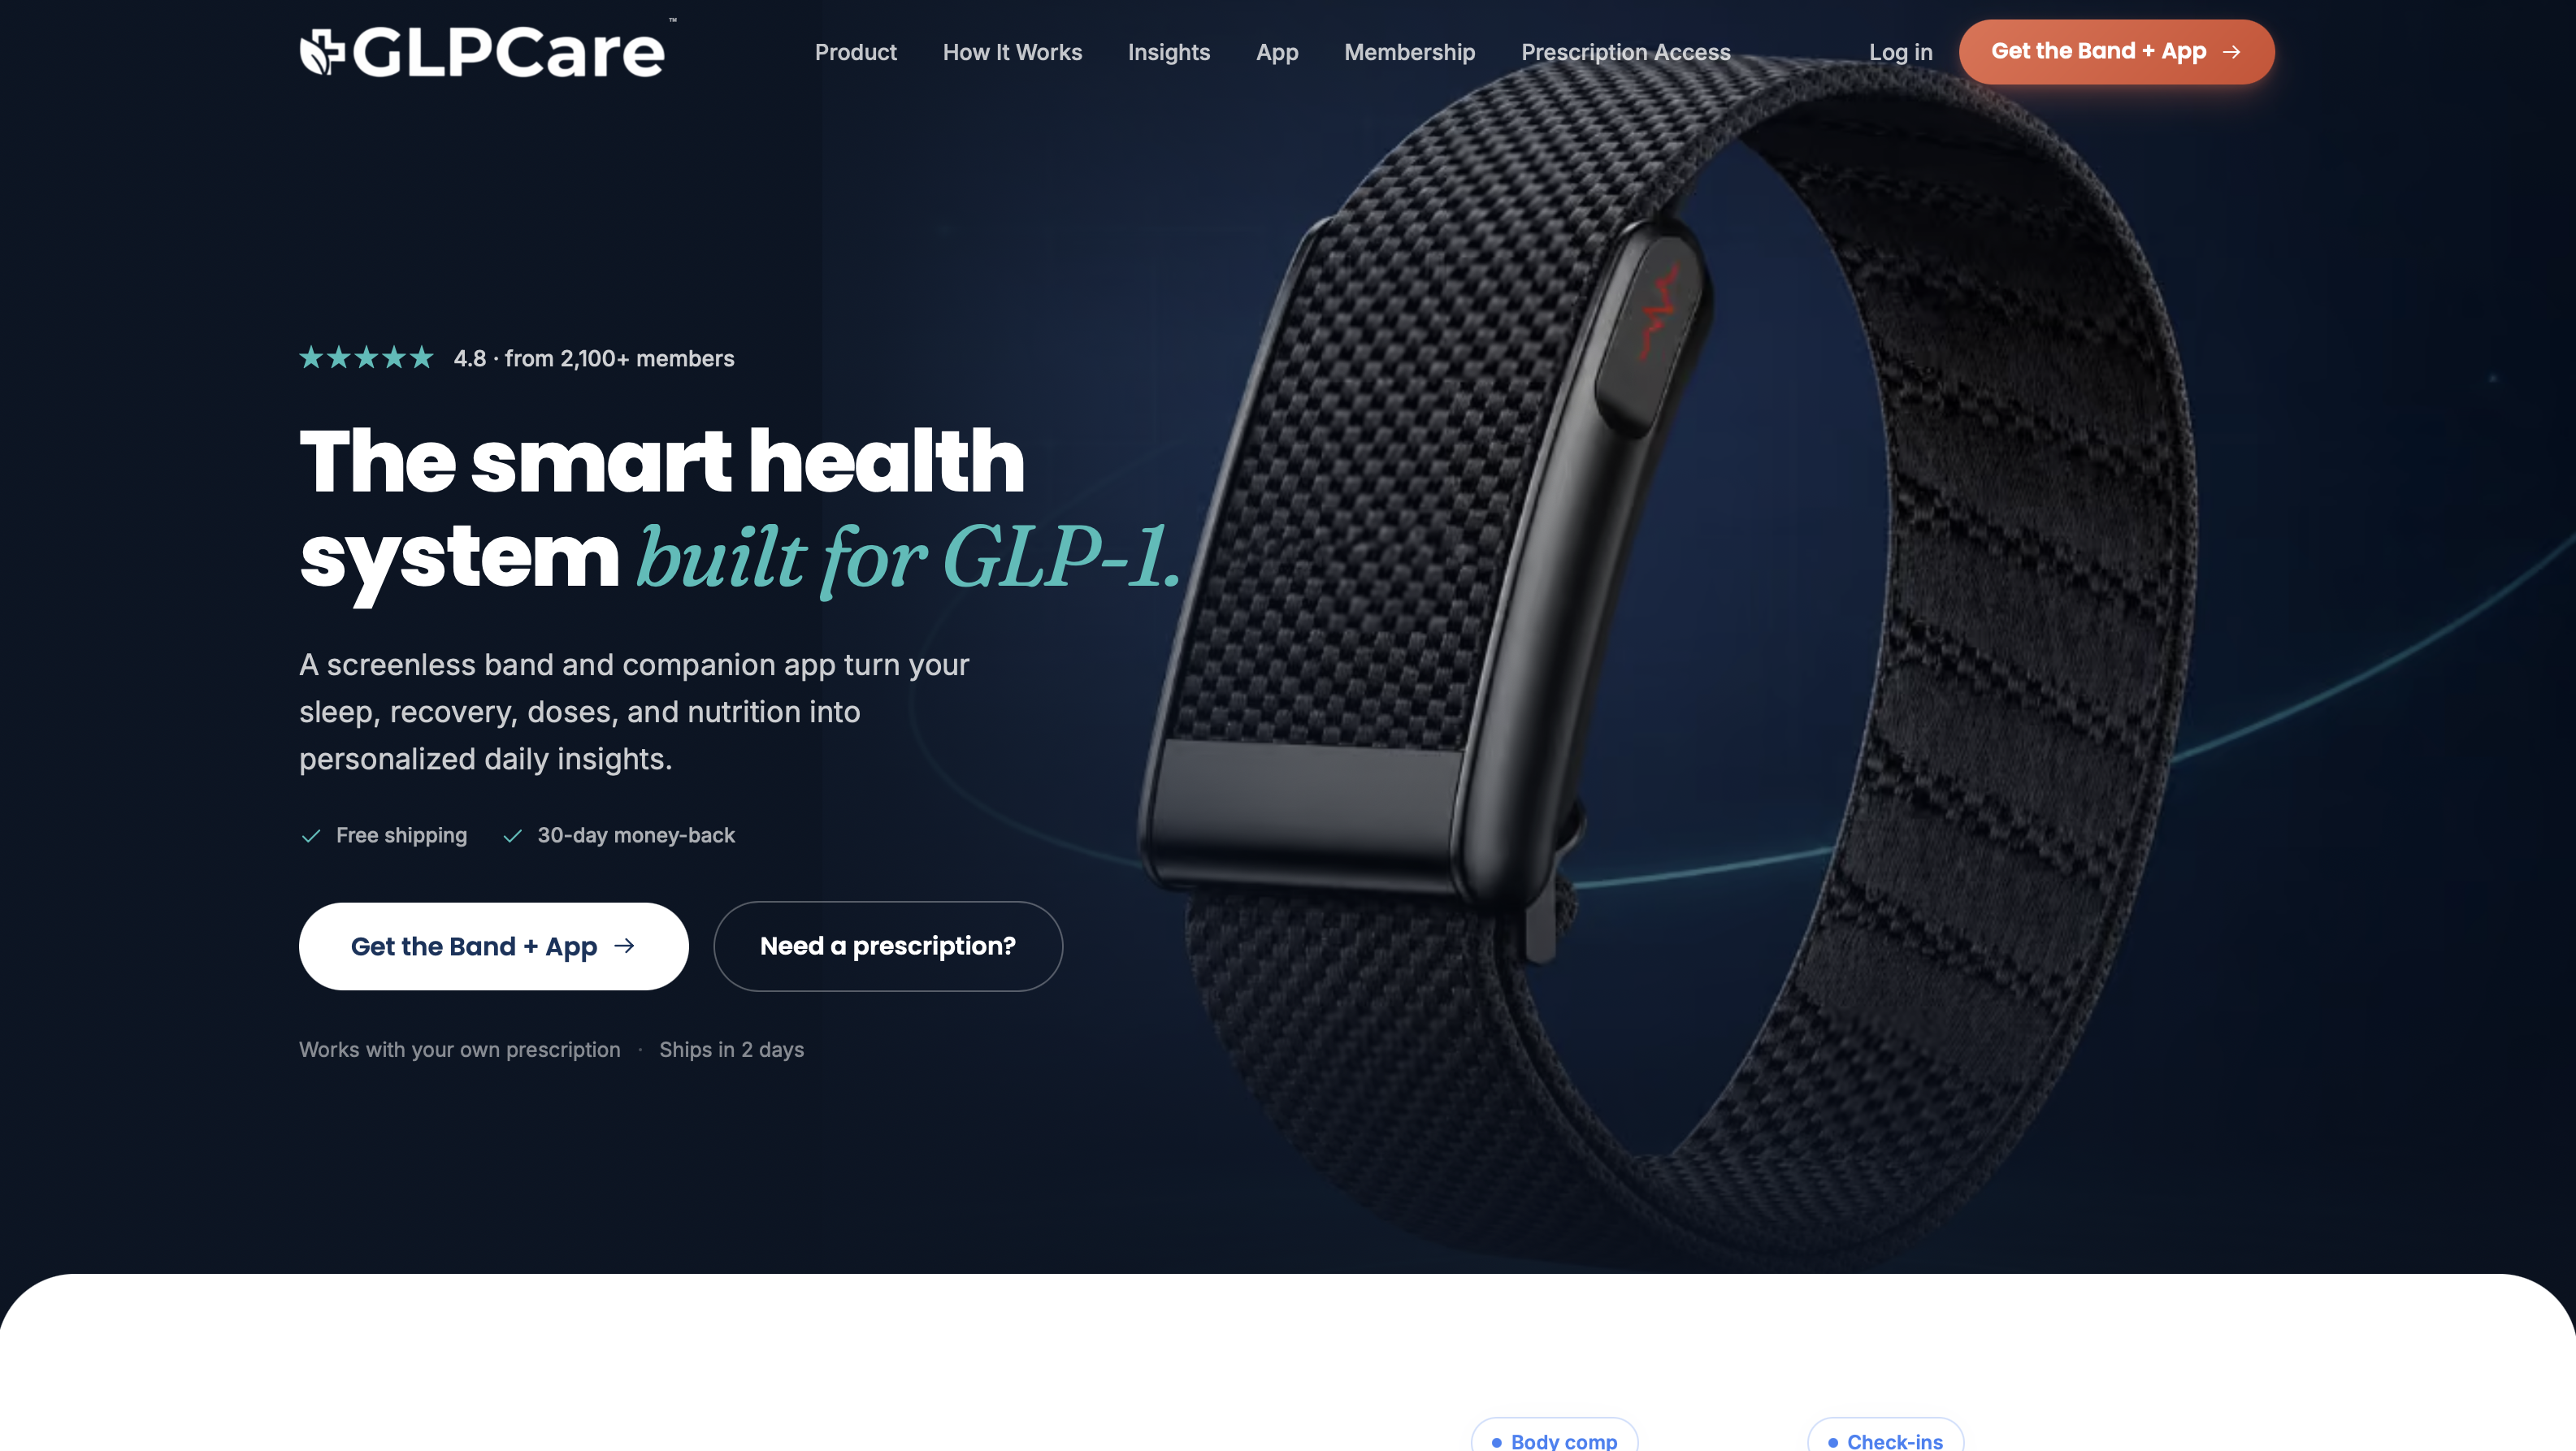
Signing up starts with an intake assessment, followed by a monitoring plan and a nutrition plan built around your current intake and goals, with regular follow-ups to adjust as you go.
- Semaglutide Care starts at $209 a month for clinician-managed prescription access.
- Compare plans, including Tirzepatide Care starting at $299 a month, to find the fit for your situation.
- GLPCare Membership is $199 a year for those who want the coaching and tracking system alongside their existing or new prescription.
If low appetite has you worried about losing muscle or falling behind on nutrition, a supervised plan catches that earlier than going it alone.
This article is general information, not a substitute for advice from a qualified doctor. Consult a qualified healthcare professional about your own circumstances before acting on anything here.
FAQ
Is it normal to have almost no appetite on semaglutide?
Reduced appetite is an expected and common effect of semaglutide, listed among its most frequent adverse reactions in FDA prescribing information. Complete loss of appetite that persists for weeks, however, is less common and should prompt a conversation with your clinician.
How long does low appetite last on semaglutide?
Appetite suppression typically begins within days of starting or increasing your dose and often eases or stabilizes over the following weeks as your body adjusts. Appetite that remains completely absent beyond four to six weeks at a stable dose is worth discussing with your prescriber.
What foods should I avoid while taking semaglutide?
Heavy, greasy, or very large meals tend to worsen nausea and discomfort because semaglutide slows gastric emptying, according to FDA labeling. Many people tolerate smaller, protein-focused meals and bland or cold foods better than rich or spicy dishes.
I’m barely eating on semaglutide. Is this normal?
Some reduction in eating is expected, but barely eating at all, especially with weight loss exceeding 5% of your body weight in a month or an inability to keep fluids down, is not something to manage alone. Contact your clinician, since dose adjustments and nutrition support can help you stay adequately nourished while still benefiting from treatment.
How long does it take to lose 20 pounds on semaglutide?
Weight loss timelines vary widely based on starting weight, dose, and individual response, and no single figure applies to everyone. A clinician who is monitoring your progress, nutrition, and dose can give you a realistic expectation based on your specific situation.
Sources
- I Am Taking a GLP-1 Weight-Loss Medication—What Should I Know? | JAMA Internal Medicine
- Pragmatic framework for lean mass and musculoskeletal preservation during GLP-1 therapy — PubMed
- Mayo Clinic Q & A: Supporting weight-loss medications with adequate, tailored nutrition - Mayo Clinic News Network