35% Smaller Meals: How Semaglutide Lowers Appetite and What to Do

35% Smaller Meals: How Semaglutide Lowers Appetite and What to Do

Semaglutide reduces appetite substantially in most people who take it, but it doesn’t switch hunger off completely. Trials show people eating roughly 24% to 35% less food at meals compared with placebo, alongside real drops in hunger ratings and food cravings. Expect quieter hunger signals, not silence.
TL;DR:
- Semaglutide reduces calorie intake by about 24% to 35% during controlled meals, primarily through lowered hunger and cravings.
- Appetite suppression typically begins two to eight weeks after starting treatment and improves with dose escalation, but persistent hunger often has behavioral or meal composition causes.
- Gastric emptying slows slightly at higher doses, but most appetite effects result from brain signaling changes affecting hunger and food reward.
- Low protein or fiber meals can cause faster digestion and early hunger spikes, which can undermine the medication’s appetite suppression.
- Any hunger returning during treatment is usually manageable with dose adjustments, meal planning, or behavioral strategies, not a sign of medication failure.
GlpcarePersonalized Support For Weight ManagementGLPCare combines GLP-1 therapy, nutrition coaching, wearable health insights, and continuous clinician support for individualized weight management.Explore GLPCare
Table of Contents
- How Much Does Appetite on Semaglutide Actually Drop?
- What Is Semaglutide Actually Doing in Your Brain?
- Why Am I Still Hungry on Semaglutide?
- When Does Semaglutide Start Suppressing Appetite?
- What Should You Eat to Manage Hunger on Semaglutide?
- When Is Low Appetite on Semaglutide a Safety Concern?
- How Do You Manage Appetite Changes With Support?
- A Straight Answer on Mixed Hunger Signals
- Ready for Clinician-Backed Support With Your Appetite?
- Primary Sources for Semaglutide and Appetite
- Sources
- FAQ
How Much Does Appetite on Semaglutide Actually Drop?
The clinical evidence here is unusually specific for a weight loss drug, which is part of why semaglutide’s appetite effects get so much attention. In a 20 week randomized trial, people taking once weekly semaglutide 2.4 mg ate about 35% fewer calories at an ad libitum buffet meal than people on placebo, 1,736 kilojoules versus 2,676 kilojoules. That’s not a rounding error. It’s a meal roughly a third smaller, measured under controlled conditions where researchers watched what participants actually chose to eat when food was placed in front of them without restriction.
A separate crossover study using a lower, 1.0 mg dose found a comparable pattern: total daily ad libitum intake across meals dropped by about 24% after 12 weeks, with meaningful weight loss to match. Two different trial designs, two different doses, and the same direction of effect. That consistency matters more than either number alone.
Here’s how the trial data breaks down across the measures researchers use most:
| Measure | Finding | Trial Duration |
|---|---|---|
| Ad libitum energy intake (2.4 mg) | ~35% lower vs. placebo | 20 weeks |
| Ad libitum energy intake (1.0 mg) | ~24% lower vs. placebo | 12 weeks |
| Hunger and satiety (CoEQ, VAS) | Reduced hunger, increased fullness | Measured across trial period |
| Food cravings | Reduced, per CoEQ scoring | Measured across trial period |
Researchers didn’t just ask people how hungry they felt. They used the Control of Eating Questionnaire and visual analog scale ratings to quantify hunger, fullness, and how much control participants felt they had over eating decisions. Those same trials recorded improved satiety scores and lower reported food cravings alongside the calorie reductions, which is why researchers describe the effect as touching both how much you eat and how much you want to eat.
The 35% figure is the headline number worth remembering: it’s the largest, most cited reduction in ad libitum energy intake from a semaglutide trial, and it came from a well controlled single meal test rather than a self reported diary.
Trial data has real limits. These studies mostly measured intake at single test meals, not full days of free living eating across months. Trial populations were also adults with obesity meeting specific enrollment criteria, so your personal response could land above or below the group averages. Ad libitum buffet tests are excellent at isolating appetite, but they’re a snapshot, not a lived week.
What Is Semaglutide Actually Doing in Your Brain?
Semaglutide is a GLP-1 receptor agonist, meaning it mimics a hormone your gut naturally releases after eating. GLP-1 receptors sit in the hypothalamus and hindbrain, the two brain regions that manage hunger, fullness, and the reward you get from food. When semaglutide activates those receptors, it changes the signaling in both regions, which is why the drug affects two separate systems at once rather than just one.

The first system is homeostatic appetite: the basic hunger and fullness signals that tell you when to start and stop eating. The second is hedonic appetite, the reward driven wanting that makes a specific food (usually something fatty, sweet, or salty) feel irresistible even after a full meal. Trial data shows semaglutide shifts food preference away from high-fat choices, suggesting the drug dampens cravings, not just stomach capacity.
Gastric emptying is the mechanism people most often assume drives semaglutide’s appetite effects, and it’s mostly a myth at maintenance dosing. Trial measurements found little to no clinically significant delay in gastric emptying at the timepoints tested. Some early, dose-dependent slowing shows up, particularly during dose escalation, but it isn’t the main engine behind the appetite suppression seen in trials. The brain signaling is doing most of the work, not a slower moving stomach.
That distinction has a practical payoff: it explains why nausea and appetite loss don’t always travel together, and why some people feel genuinely less hungry with minimal digestive slowdown while others notice more gut based symptoms early in treatment.
Why Am I Still Hungry on Semaglutide?
Persistent hunger on semaglutide is common, and it almost always traces back to one of a handful of causes rather than the medication “not working.” Some published reports note that subjective hunger can partly return over months of treatment even while measured calorie intake stays lower than before starting. Feeling hungry and eating more aren’t the same thing.
The most frequent explanations:
- You’re early in dose escalation. Semaglutide starts low and increases roughly every four weeks, and appetite suppression typically lags behind each step up.
- You’re in a pharmacokinetic trough. Blood levels dip in the days before your next weekly dose, and some people feel a predictable hunger bump right before their next injection.
- Your body is adapting. Some tolerance to appetite suppression can develop over months, a known pattern with GLP-1 therapy generally.
- The hunger is behavioral, not physical. Emotional eating and habitual triggers, like snacking during a stressful call or eating out of boredom, don’t disappear just because a hormone pathway changed. Psychological drivers of eating behavior often need their own strategy, separate from medication.
- Your meals digest too fast. Low-protein, low-fiber meals move through your system quickly and bring hunger back sooner, even at a full dose.
Pro Tip: Keep a simple daily log of when hunger spikes hit during your dosing week. If you notice a pattern, like feeling ravenous on days 5 and 6, that’s a pharmacokinetic trough, not a failure of the medication, and it’s worth mentioning to your prescriber.
Think of semaglutide as a volume control on appetite signals, not a mute button. It turns hunger down. It doesn’t turn off the biological need to eat, and it was never designed to.
When Does Semaglutide Start Suppressing Appetite?
Most people notice a real drop in appetite somewhere between two and eight weeks after starting, and the timing tracks closely with the dose escalation schedule. Semaglutide starts at a low dose specifically to reduce nausea risk, and appetite suppression at that starting dose is usually mild. The stronger effects trial data documents, the 24% to 35% intake reductions, showed up at higher maintenance doses like 1.0 mg and 2.4 mg, not at the starting dose.
Each time your dose steps up, expect a short adjustment window before the appetite effect stabilizes at that new level. Steady state effect, meaning the point where your body has fully adjusted to a given dose, generally takes several weeks after reaching a maintenance dose, not days.
If you’ve been at your maintenance dose for six to eight weeks with no noticeable change in hunger or intake, that’s a legitimate signal worth raising with your clinician, not something to just push through. It could mean your dose needs adjusting, or that behavioral factors are outweighing the medication’s effect. Either way, it’s a conversation, not a guess. Some people also find it useful to compare their experience against structured intermittent fasting approaches built specifically around GLP-1 dosing timing.
What Should You Eat to Manage Hunger on Semaglutide?
Meal composition determines a lot of your day-to-day hunger experience, arguably more than most people expect once they’re already on the medication. Cleveland Clinic’s GLP-1 nutrition guidance points to protein and fiber as the two biggest levers for satiety, and it lines up with what appetite trial data shows about slower digesting meals producing longer lasting fullness.
Four practical moves make the biggest difference:
- Front-load protein at breakfast. Eggs, Greek yogurt, or a protein shake keep you fuller longer than a carb-heavy start to the day, and they help preserve muscle mass during weight loss.
- Build fiber and volume into every meal. Vegetables, legumes, and whole grains take up physical space in your stomach and slow digestion, which stretches out the feeling of fullness.
- Carry portable protein for pre-dose hunger windows. A hard boiled egg or a small container of cottage cheese solves the trough hunger problem better than skipping the snack entirely.
- Adjust portion size before you adjust meal frequency. If you’re not hungry for a full meal, shrink the plate rather than skipping the meal altogether. Undereating for days at a time creates its own problems.
Sleep and stress deserve real attention here too. Poor sleep and chronic stress both push hunger hormones in the wrong direction, working against whatever appetite suppression the medication is providing. Add resistance training two to three times a week if you can manage it. It’s one of the more reliable ways to protect lean muscle while you’re in a calorie deficit, and pairing it with adequate protein intake matters more on semaglutide than off it.
Pro Tip: If you notice hunger cues that have nothing to do with your stomach, like reaching for food after a hard conversation, write down the trigger before you eat. That single pause is often enough to tell the difference between physical hunger and an emotional cue, and it’s a strategy counselors use specifically with GLP-1 patients.
When Is Low Appetite on Semaglutide a Safety Concern?
Nausea, mild constipation, and occasional reflux are the most common side effects tied to appetite changes on semaglutide, and they usually respond to smaller, slower meals and staying upright after eating. Acid reflux specifically tends to improve as your body adjusts to a given dose.
Some signs mean it’s time to call your prescriber rather than wait it out: rapid, unintended weight loss beyond what your care plan targets, dizziness or fainting, signs of electrolyte imbalance, or vomiting that doesn’t let up. Appetite suppression that’s so strong you’re skipping meals entirely for days deserves a conversation, not silent endurance.
If you’re managing diabetes with insulin or a sulfonylurea alongside semaglutide, reduced food intake raises real hypoglycemia risk, and your care team may need to adjust those other medications. The FDA prescribing information documents this interaction directly, and it’s worth reviewing alongside any other medications you take. Check known drug interactions with your prescriber before starting or adjusting any dose.
How Do You Manage Appetite Changes With Support?
A comprehensive program to address persistent hunger typically includes clinician dose management, nutrition coaching, and wearable tracking of sleep, heart rate, and activity. Those three signals together, not just your weight, show whether hunger is a dosing issue, a trough pattern, or a meal composition problem.
An AI companion app can integrate logged dose timing, food intake, and biometric data to help identify patterns such as pre-dose hunger spikes or sleep-related cravings, offering continuous context beyond infrequent office visits.
A Straight Answer on Mixed Hunger Signals
Clinical patterns on semaglutide are rarely all-or-nothing. Some people report near total appetite suppression within weeks; others notice a partial dampening that still leaves room for hunger, especially before a dose. Both patterns show up in trial data, and neither one means the medication has failed. Track your hunger against your dosing schedule and your meals, and bring that record to your clinician rather than guessing alone.
— Dominique
Ready for Clinician-Backed Support With Your Appetite?
Many diet apps and generic weight loss plans treat hunger as a willpower problem. Integrated programs connect prescribed doses, meals, and biometrics so clinicians can better understand the causes of persistent hunger rather than relying on guesswork from single check-ins.
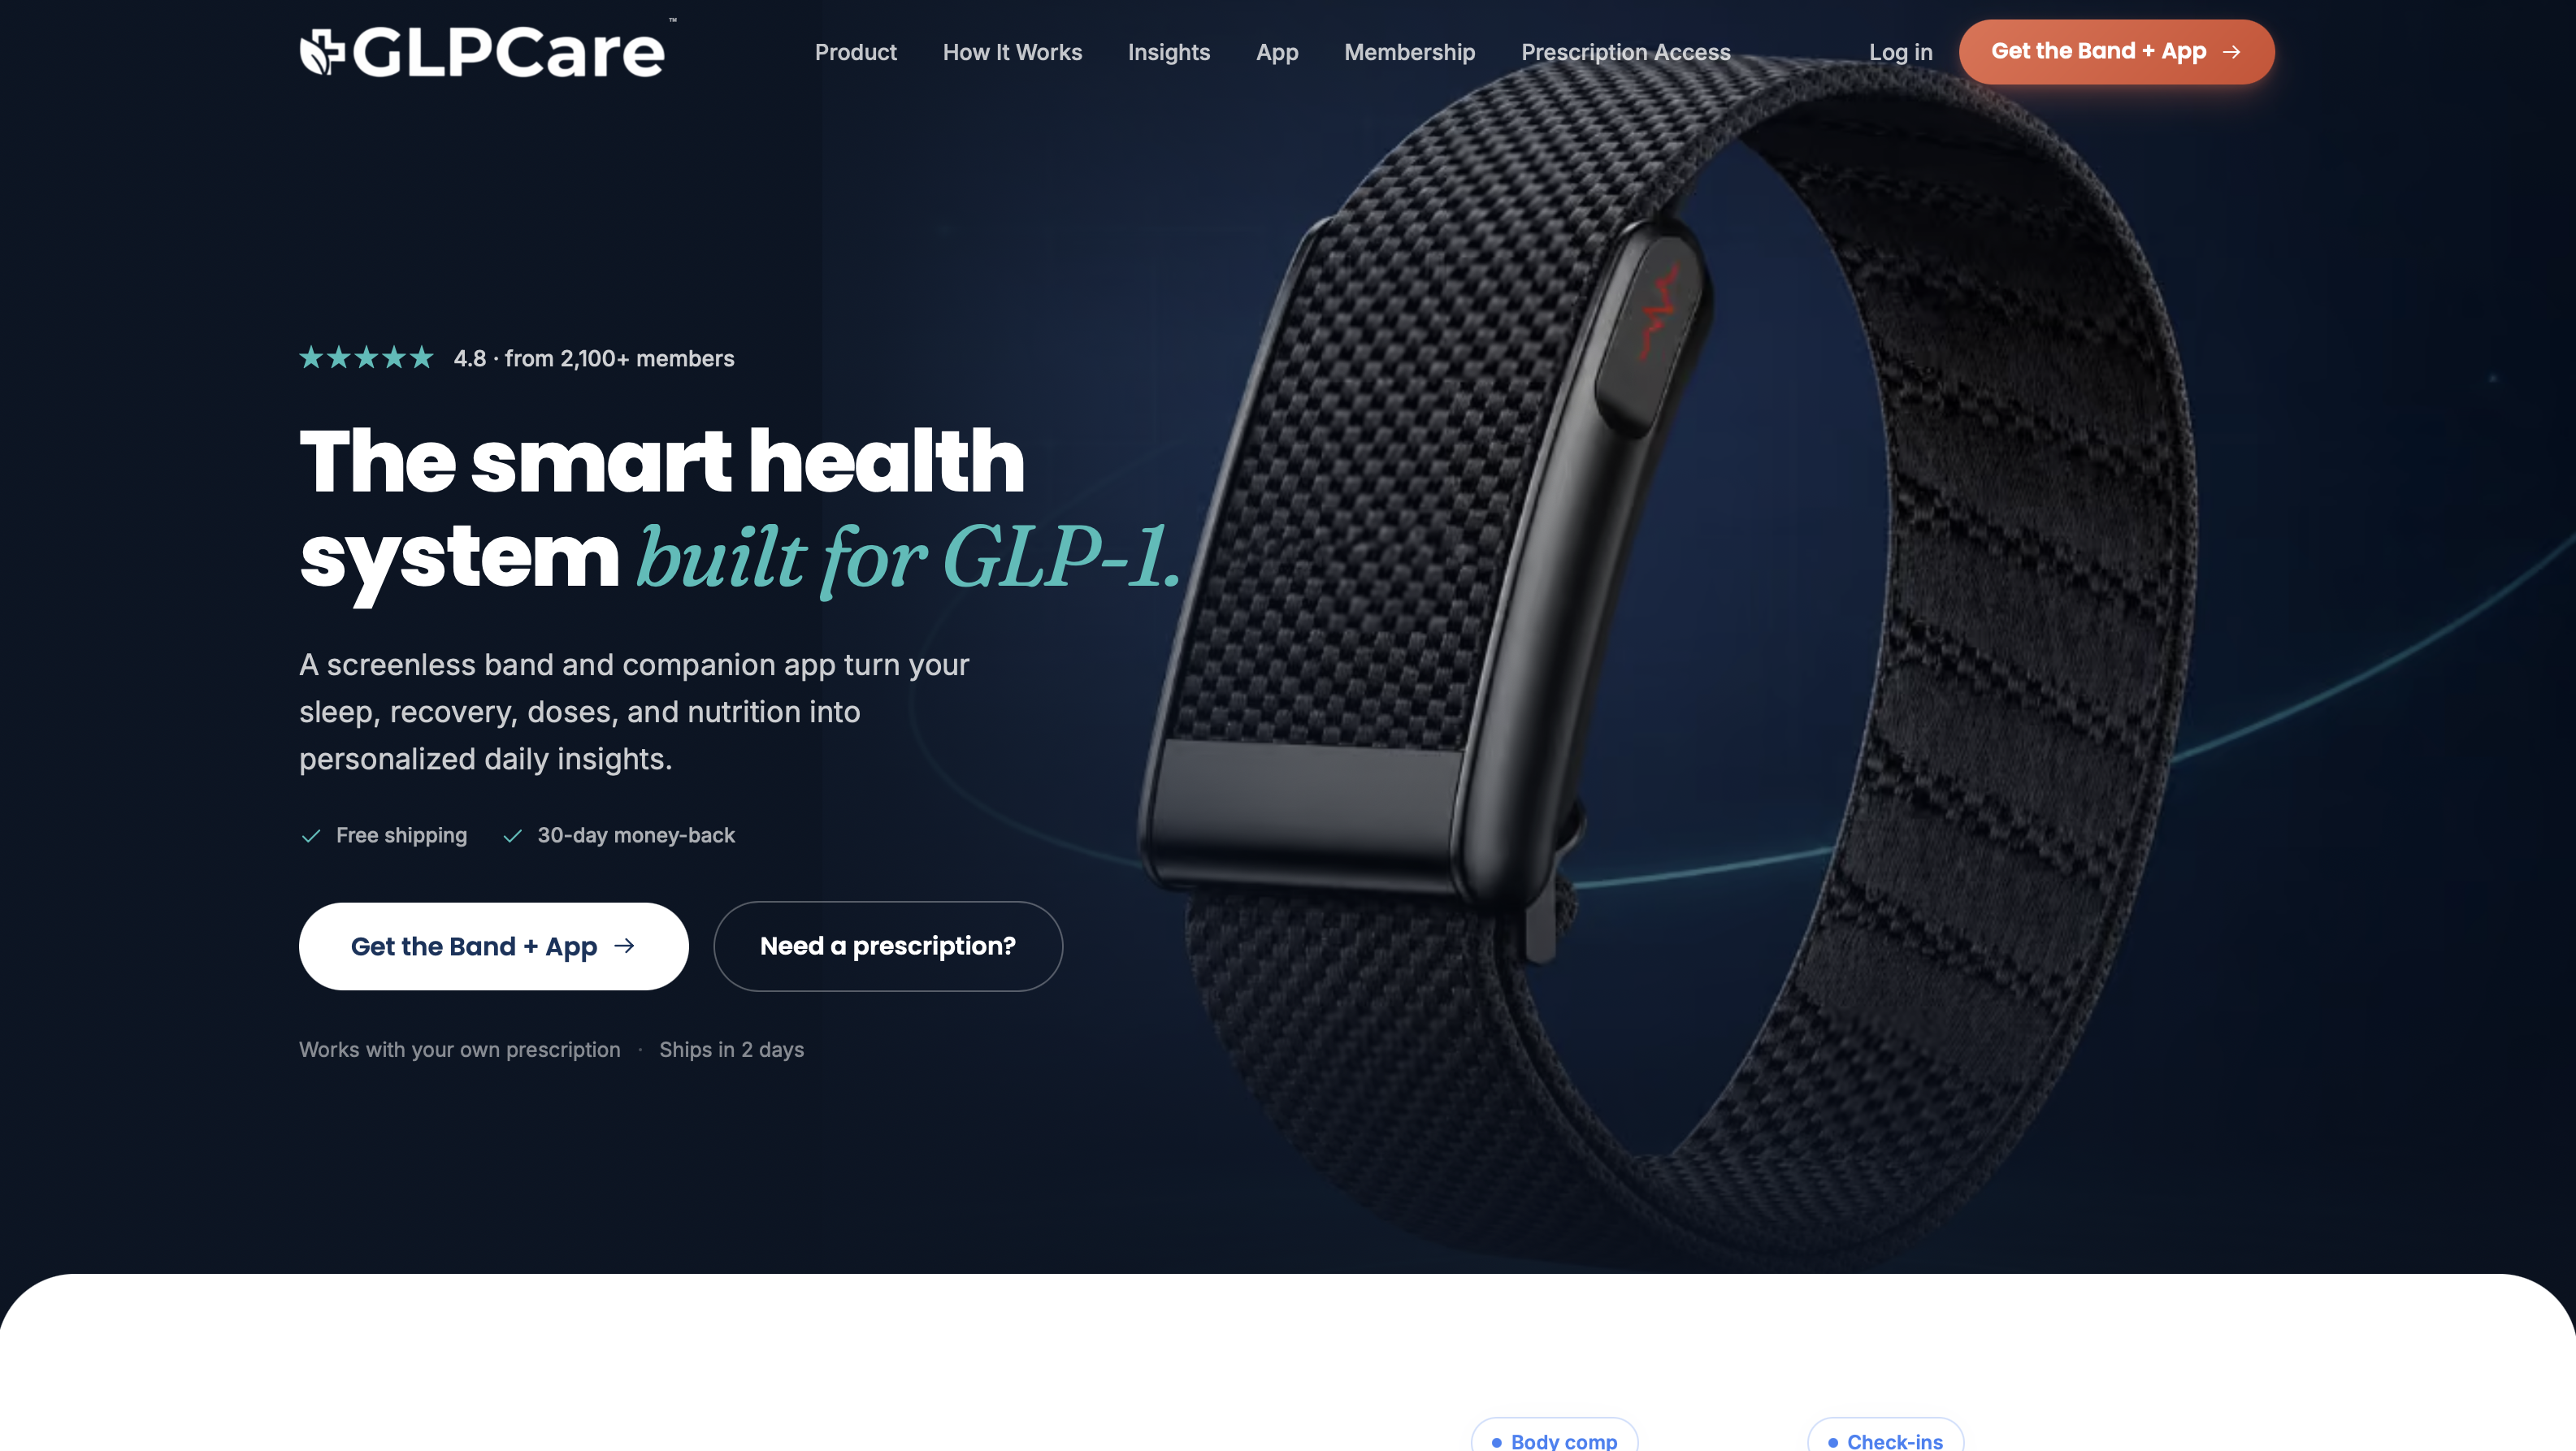
The GLPCare Membership runs $199 per year and includes access to the coaching and tracking system built around your care plan. If you need a prescription, Semaglutide Care starts from $209 per month with clinician oversight built in, and Tirzepatide Care starts from $299 per month for those who’ve discussed that option with a provider. Pair either plan with the screenless GLP Care Band to track sleep, heart rate, and activity alongside your dose. Start by reviewing your options and choosing the plan that matches where you are in treatment.
Primary Sources for Semaglutide and Appetite
- Ad libitum energy intake and appetite trial (semaglutide 2.4 mg)
- Control of eating and gastric emptying findings
- Crossover trial on appetite, intake, and food preference
- Clinicaltrials
This article is general information, not a substitute for advice from a qualified doctor. Consult a qualified healthcare professional about your own circumstances before acting on anything here.
Sources
- The effect of semaglutide 2.4 mg once weekly on energy intake, appetite, control of eating, and gastric emptying in adults with obesity
- The effect of semaglutide 2.4 mg once weekly on energy intake, appetite, control of eating, and gastric emptying in adults with obesity (PubMed entry)
- Effects of once‐weekly semaglutide on appetite, energy intake, control of eating, food preference and body weight in subjects with obesity
- Clinicaltrials
FAQ
Why Am I Getting Hungry on Semaglutide?
Hunger on semaglutide usually comes from one of a few sources: early dose escalation, a pharmacokinetic trough before your next weekly dose, or meal choices low in protein and fiber that digest too quickly. Trial data shows the medication lowers overall intake even when subjective hunger occasionally returns, so some hunger doesn’t mean the drug has stopped working.
Why Isn’t Semaglutide Curbing My Appetite?
If appetite suppression hasn’t kicked in after six to eight weeks at your maintenance dose, the cause is often behavioral eating, an underdosed step in escalation, or meals that don’t include enough protein and fiber. Bring a hunger log tied to your dosing schedule to your clinician, since that pattern usually points to the exact fix needed.
Does Semaglutide Burn Fat or Just Suppress Appetite?
Semaglutide’s primary documented mechanism is appetite and intake reduction, not direct fat burning. Weight loss happens because trial participants consistently ate less at a calorie deficit over time, which is the same fundamental mechanism behind most sustained weight loss.
Does Semaglutide Work if You Don’t Overeat?
Semaglutide can still support weight loss in people who don’t habitually overeat, since it also affects satiety and food reward, not just portion size. The effect may simply feel smaller if your baseline intake was already moderate, which is worth discussing with a clinician when setting realistic expectations.
What Does Glpcare Cost for Semaglutide Care?
Semaglutide Care through Glpcare starts from $209 per month, and the GLPCare Membership is $199 per year for the coaching and tracking system. Exact pricing details and plan comparisons are available on the Glpcare comparison page.